



For a long time, fungal infections have meant itchy skin, discoloured nails and sometimes hair loss.
These symptoms are collectively called dermatophytosis and are caused by a group of fungi called dermatophytes.
‘’Unfortunately, immunocompromised patients can get lesions all over their body. The itchiness and the lesions can get so severe that people even get suicidal thoughts,” said Shivaprakash Rudramurthy, professor of medical mycology at the Postgraduate Institute of Medical Education and Research (PGIMER), Chandigarh.
Global warming
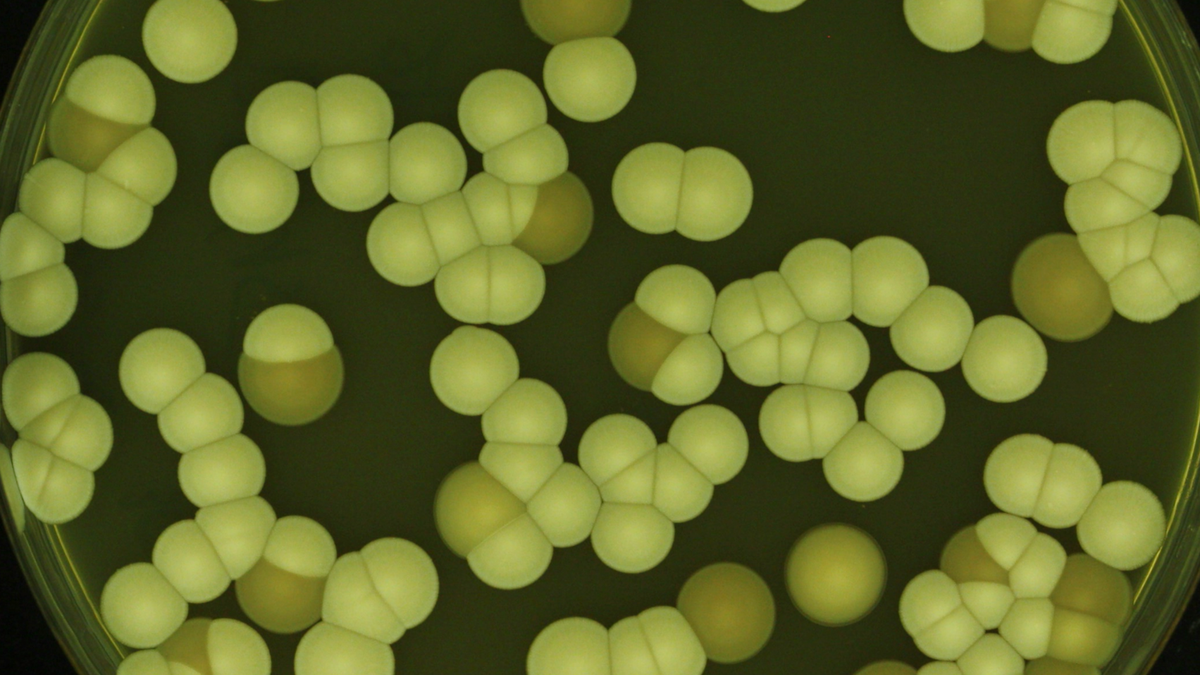
Dermatophytes are molds: fungi that grow in long strands. The other common category of fungi is yeast, which are single, oval-shaped cells. Among the yeasts, Candida auris is rapidly emerging as a multidrug resistant pathogen in ICU facilities. It enters the blood stream and causes severe infections, most of which are untreatable by the available antifungals. According to Prof. Rudramurthy, those infected suffer a 30-40% mortality rate.
C. auris has become a menace only in the last two decades. The first report was in 2009 in Japan. Several other fungal species have become more pathogenic only in recent times. The cause of this rise remains unresolved but scientists and medical doctors have some ideas.
Fungi grow best in damp places below 30° C, so they can grow on our skin, especially in moist areas of the body, like armpits and the genital area. However, bloodstream infections in humans were rare because they could not survive in the body’s 37° C temperature.
“Fungal infections are common in cold-blooded animals with lower body temperatures,” Sriram Varahan, a mycologist at CSIR-Centre for Cellular and Molecular Biology, Hyderabad, said.
“But global warming puts a selective pressure on fungi such that only the more heat-tolerant ones survive. These ones can survive inside our bodies too, if they gain access to it. This is called the fungal infection — mammalian selection hypothesis.”
Clinical samples
Today, roughly 20% of infections reported in hospitals are fungal in nature — yet most hospitals in India lack the capabilities and infrastructure to identify fungal pathogens, Prof Rudramurthy said.
This prompted PGIMER to begin storing fungal pathogens some 25 years ago. Today, the institute holds a stock of 15,000 clinical fungal isolates across India and helps other medical centres and clinicians identify and culture them for study, free of cost.
The C. auris isolates from PGIMER’s repository have come handy for Kaustuv Sanyal and his research associate Aswathy Narayanan, both at the Jawaharlal Nehru Centre for Advanced Scientific Research, Bengaluru. They study how fungal pathogens divide and their genomes evolve.
In a recent study published in Nature Communications, they characterised the clinical isolates of C. auris found across India. Their focus was the pathogen’s ability to resist antifungals. They were able to establish their findings in patient samples and go beyond earlier studies in model systems.
“More than 90% clinical isolates of C. auris are resistant to common azole-based antifungals, such as fluconazole,” Prof. Sanyal said. Some “30% of them are resistant to another class of antifungals called the polyenes. They mostly respond to a different class of antifungals called the echinocandins.”
A drug may not work on a pathogen for many reasons, including the drug’s target becoming mutated or the drug’s effect being negated by the pathogen’s own biomolecules. Dr. Narayanan and her collaborators at the Indian Institute of Science Education and Research, Thiruvananthapuram, found significant changes in drug-resistant C. auris genomes that could explain why Indian clinical isolates were able to resist azoles and echinocandins.
Susceptibility tests
A fungal cell has two protective layers surrounding it. The outermost is the cell wall and the inner one is the cell membrane. Azole and polyene antifungals target a fat called ergosterol that is enriched in the cell membrane. Echinocandins target the cell wall.
“When we grow C. auris isolates in the presence of fluconazole, the pathogen fights back by making extra copies of the Erg 11 gene. This in turn helps in higher production of ergosterol, thereby eliminating the effect of the azole drug,” Dr Narayanan said.
The study found parts in the C. auris genome where additional copies of the Erg11 gene were present.
With echinocandin drugs such as caspofungin, the team found mutations in the Fks1 gene that allowed the pathogen to resist the drug’s action. The team also found genetic changes promoting higher tolerance of echinocandins.
“Fks1 mutations can enable C. auris to survive even caspofungin doses up to 16 ug/ml. That means a patient with such a pathogen will need the drug at a concentration higher than 16 ug/ml,” Prof. Sanyal said. “Today, clinicians would not know that because they test the pathogen’s ability to survive only until 2 µg/mL of caspofungin — as defined by the U.S. Centers for Disease Control and Prevention, and followed globally.”
The logical thing for clinicians would be to look for mutations like in the Fks1 gene and decide the limits for tests to decide the antifungal dose for patients. But due to associated costs, a more practical way is to increase the limits of susceptibility tests for caspofungin to higher than 16 ug/ml, Prof. Sanyal added.
C. auris, without any specific gene mutation or gene duplication, still responds to high concentrations of caspofungin in unexpected ways. While the pathogen dies at lower concentrations of the drug, at exceptionally high ones, it survives. This is paradoxical.
“This is because caspofungin at high doses activates compensatory pathways in the fungus,” Prof. Sanyal explained. “The fungus starts producing chitin, the raw material of the fungal cell wall, in large quantities. Any damage that caspofungin brings about on the cell wall is compensated by the extra chitin production. And thus the cell wall remains intact despite the antifungal.”
Such examples of paradoxical growth are called the Eagle effect, named for the U.S. pathologist Harry Eagle.
Beyond the arms race
The studies underline the importance of clinicians conducting more nuanced susceptibility tests to decide the antifungal doses. They show that fungi are protected from antifungals by genetic mutations as well as by making more copies of protective genes.
Prof. Sanyal also stressed on the need for a combination of therapies to target cellular compensatory pathways, keeping the major antifungals effective against drug-tolerant species.
However, Dr. Varahan said he believed scientists and doctors need to think of gentler alternatives: “When we target [a molecule] without which an organism cannot live at all, evolution ensures that its population survives with a changed molecule. So instead of participating in an arms race, it is perhaps better to target the less critical molecular pathways, inhibition of which will allow the pathogen to still survive but not cause a disease.”
It seems the idea of dousing fungal pathogens with antifungals is nearing its end. The next-generation of antifungals will need more planning.
Somdatta Karak heads science communication at CSIR-CCMB.
